
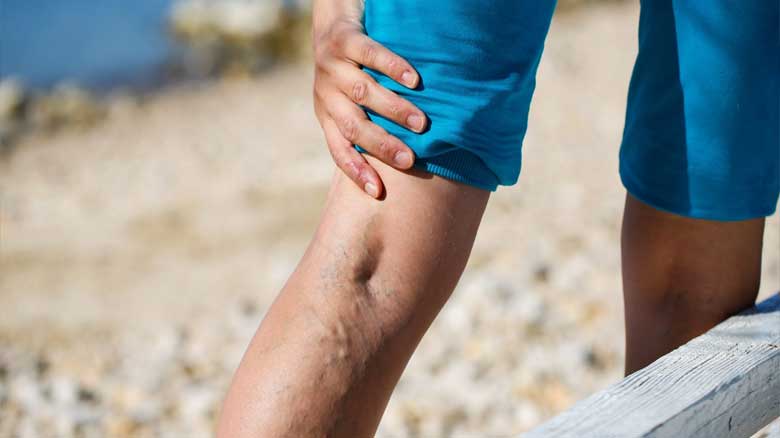
Varicose veins are enlarged, twisted veins just under the skin of the legs. They develop when the one-way valves inside the veins stop closing properly, so blood pools instead of returning to the heart. Around one in four adults has them, and for many people they are a cosmetic issue and nothing more. For others, they are the visible sign of a problem that is slowly damaging the skin of the leg. The difference is not always obvious from the outside, which is why the question "should I see someone about this?" is worth answering carefully.
Signs you can reasonably watch
- Visible veins that do not hurt, do not swell and have not changed for years
- Mild aching or heaviness at the end of a long day on your feet, relieved by putting the legs up
- Thread veins (fine red or purple lines) without other symptoms
If this describes you, compression stockings, regular walking, avoiding long periods of standing still and keeping weight in check are reasonable first steps. Treatment is available if the appearance bothers you, but it is a choice rather than a necessity.
Signs that mean it is time to see a vascular surgeon
- Swelling of the ankle or lower leg that is worse in the evening and improves overnight
- Skin changes above the ankle - brown staining, itching, eczema, or skin that feels hard and tight. This is the stage before an ulcer forms.
- A wound near the ankle that will not heal - a venous leg ulcer. Once this happens, treating the veins is no longer optional.
- Bleeding from a vein after a minor knock. Lie down, raise the leg and press on it; then get it assessed.
- A hard, painful, red lump along a vein - superficial thrombophlebitis, a clot in the varicose vein. It needs assessment because it can extend into the deep veins.
- Pain, aching or cramping that limits your work or sleep
- Varicose veins after a previous deep vein thrombosis
Sudden swelling of one whole leg with pain, or calf pain with breathlessness, is different - that can be a deep vein thrombosis and needs emergency attention, not a routine appointment.
What the assessment involves
There is no waiting for it to get worse. The key test is a duplex ultrasound scan of the leg veins, done in the clinic: painless, about twenty minutes, no needles. It shows which valves have failed, whether the deep veins are healthy, and where the faulty vein needs to be closed. With that map, the surgeon can tell you whether treatment is advisable, optional or unnecessary, and which method suits your veins.
Treatment has changed
The old operation - "stripping" the vein under general anaesthesia, with a hospital stay and weeks of recovery - is rarely needed now. Modern treatment closes the faulty vein from the inside through a tiny puncture, under local anaesthesia, and you walk out the same day:
- Endovenous laser or radiofrequency ablation - heat seals the vein shut.
- Medical adhesive (glue) - the vein is closed with a special glue, with no heat and usually no compression stockings afterwards.
- Foam sclerotherapy - a foam injected into smaller veins closes them; often used alongside the other methods.
- Microsclerotherapy - tiny injections for thread veins.
Most people return to normal activity within a day or two. Our vascular surgeon offers all of these; the choice depends on the scan, not on preference alone. See varicose vein treatment for what to expect before and after.
Common questions
Will the veins come back? A treated vein does not reopen, but new varicose veins can develop over the years in people with the tendency. Follow-up scans catch them early.
Do I need the vein? No. Varicose veins carry blood the wrong way; closing them redirects flow into healthy veins and improves circulation.
Is treatment safe in diabetes or older age? Usually yes, because these procedures avoid general anaesthesia. The assessment checks the arteries of the leg as well, which matters in people with diabetes.
Read more about varicose veins and leg ulcers.


